
NABH HOPE Rule Change 2026: What 300+ Bed Hospitals Must Do
October 16, 2026Tier-2 & Tier-3 Hospital Investment in India: The 2026 Case
October 19, 2026PMJAY De-Empanelment: How to Protect Your Hospital in 2026

PMJAY De-Empanelment: How to Protect Your Hospital’s Empanelment in 2026
States have de-empanelled 2,359 hospitals from Ayushman Bharat PM-JAY and suspended a further 1,200, while ₹676.14 crore of claims has been blocked. Most of those actions are documentation and systems failures rather than fraud — this guide sets out the five triggers and the seven controls that protect your empanelment.
class="attachment-full size-full wp-image-6875" alt="" srcset="https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6.png 500w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-300x300.png 300w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-150x150.png 150w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-75x75.png 75w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-480x480.png 480w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-24x24.png 24w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-36x36.png 36w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-6-48x48.png 48w" sizes="(max-width:767px) 480px, 500px" /> Dr. Vishal Jadhav · Founder, Hospertz

16 October 2026 6 min read
class="attachment-full size-full wp-image-6889" alt="" srcset="https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz.webp 1200w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-300x158.webp 300w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-1024x538.webp 1024w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-768x403.webp 768w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-143x75.webp 143w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-480x252.webp 480w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-24x13.webp 24w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-36x19.webp 36w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-de-empanelment-hospital-compliance-2026-hospertz-48x25.webp 48w" sizes="(max-width:767px) 480px, (max-width:1200px) 100vw, 1200px" /> In this article
- As of 31 May 2026, 2,359 hospitals had been de-empanelled and 1,200 suspended; ₹676.14 crore in claims was blocked by 31 July 2026.
- Most de-empanelments are documentation and systems failures that look like fraud to an automated system — which means the fix is operational.
- ABHA capture at registration, not at discharge, is the single highest-value control you can enforce in software.
- Taking any deposit from a beneficiary — even refunded later — breaches the empanelment MoU and is one of the fastest routes to suspension.
- A documented history of monthly self-audit is substantial evidence of good faith if you are ever investigated.
Ayushman Bharat PM-JAY is now the largest single source of inpatient volume in Indian healthcare. As of 28 February 2026, 36,229 hospitals were empanelled — 19,483 public and 16,746 private — and 11.69 crore hospital admissions had been authorised since the scheme began.
But the scheme has tightened sharply. As of 31 May 2026, states and union territories had de-empanelled 2,359 hospitals and suspended a further 1,200 for guideline violations. By 31 July 2026, authorities had blocked fraudulent claims worth ₹676.14 crore.
For a private hospital that has built its occupancy model around PMJAY volume, de-empanelment is not a compliance inconvenience. It is a revenue event.
This post covers what is actually triggering these actions, and the systems that protect you.
The enforcement environment has changed
Three things happened in parallel, and together they changed the risk profile of PMJAY participation.
Automated fraud detection went live at scale. The National Anti-Fraud Unit now flags suspicious claim patterns within 24 hours of submission. The triggers include unauthorised billing, duplicate entries, inflated procedure costs and identity mismatches. This is pattern detection across a national dataset — not a human reading your file. A hospital whose billing profile sits outside the norm for its peer group gets flagged whether or not anyone intended fraud.
The empanelment framework was formalised. The AB PM-JAY Hospital Empanelment and De-Empanelment (HEM) Guidelines were issued in July 2026, setting out disciplinary proceedings and de-empanelment provisions in structured form. These provisions have also been adopted by reference into other schemes, including PM-RAHAT.
Digital integration became a precondition. ABDM integration is now effectively mandatory for empanelment and for claims processing. Hospitals that are not ABDM-compliant face claim rejections and risk de-empanelment.
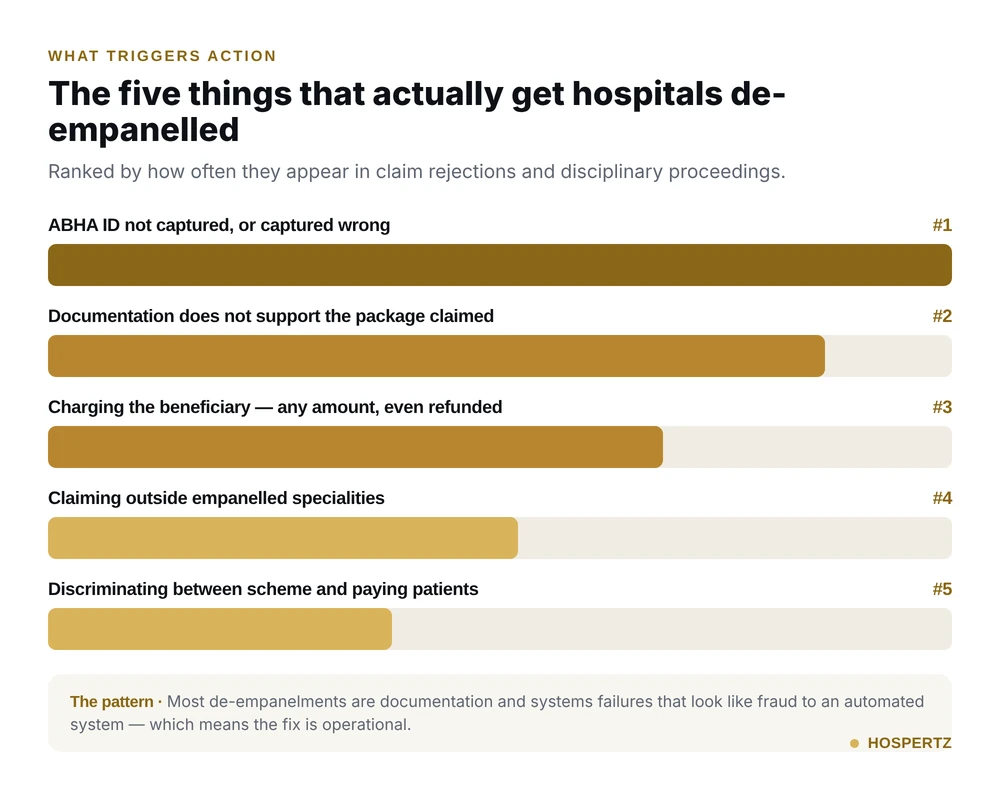
The key thing to understand is that most de-empanelments are not fraud in any meaningful sense. They are documentation and systems failures that look like fraud to an automated system. That distinction matters, because it means the fix is operational, not ethical.
Five things that actually get hospitals de-empanelled
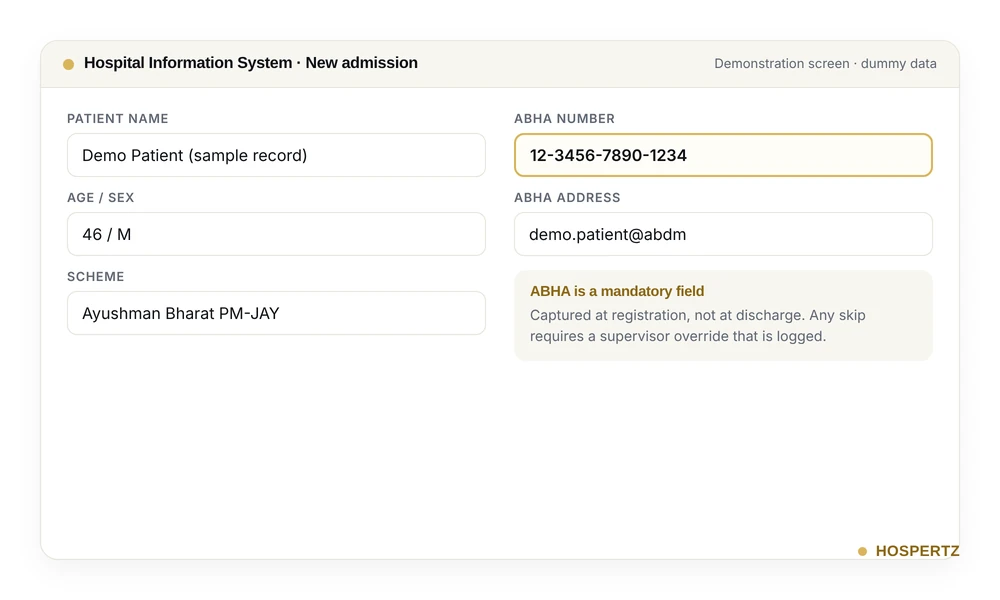
- ABHA ID not captured, or captured wrong. Patients must be registered using their ABHA (Ayushman Bharat Health Account) ID at admission. A front desk that treats this as optional, or that enters it hurriedly at discharge, generates mismatches between the claim and the national health record — which reads as identity irregularity.
- Clinical documentation that does not support the package claimed. Every HBP code implies a clinical pathway. If you claim a surgical package, the file must contain the operative notes, the anaesthesia record, the implant details and the discharge summary that correspond to it. Thin files on high-value packages are the single most reliable way to attract an audit.
- Charging the beneficiary. The hospital cannot ask the beneficiary for any additional payment. Any “deposit” — even one taken in good faith and refunded later, even one collected by a ward clerk without management’s knowledge — is a violation of the empanelment MoU. This is one of the fastest routes to suspension because beneficiaries complain about it directly.
- Claiming outside your empanelled specialities. Empanelment does not mean every procedure at your hospital is covered. It covers the listed specialities and HBP codes only. Hospitals that add a speciality, start treating under it, and claim before the empanelment scope is formally updated create a straightforward mismatch.
- Discriminating between PMJAY and paying patients. Denying admission to PMJAY beneficiaries while admitting paying patients is a documented complaint category and is actively investigated. “Beds are full” is not a defence when the inspection record shows otherwise.
class="attachment-full size-full wp-image-6888" alt="" srcset="https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart.webp 1000w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-300x240.webp 300w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-768x614.webp 768w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-94x75.webp 94w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-480x384.webp 480w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-24x19.webp 24w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-36x29.webp 36w, https://www.hospertz.com/wp-content/uploads/2026/10/pmjay-claim-rejection-top-reasons-chart-48x38.webp 48w" sizes="(max-width:767px) 480px, (max-width:1000px) 100vw, 1000px" /> Chart showing the most common reasons PMJAY claims are rejected and hospitals de-empanelled
The seven systems that protect you
If you run PMJAY volume, these need to exist as systems — not as the diligence of one good person who might leave.
- ABHA capture at the point of registration, enforced by software. Make the ABHA field mandatory in your HIS at admission. If it cannot be captured, the admission should require a supervisor override that is logged. Train every front-desk shift, not just the day shift.
- A pre-submission claim checklist. Before any claim is submitted, a single named person verifies: ABHA linked, package code matches the documented procedure, all supporting documents attached, speciality within empanelled scope, no beneficiary payment taken. This one control eliminates the majority of avoidable rejections.
- A zero-deposit policy with signage and audit. Display the no-payment rule visibly in the admission area in the local language. Audit your receipt book monthly against PMJAY admissions. Any receipt matched to a PMJAY beneficiary gets investigated immediately.
- Monthly internal claim audit. Pull a random sample of ten submitted claims per month and audit them against the clinical file as though you were the auditor. Document what you found and what you fixed. If you are ever investigated, a history of self-auditing is substantial evidence of good faith.
- Speciality scope reconciliation each quarter. Compare the specialities you are actively claiming under against your formal empanelment scope. Update the scope before you start claiming, not after.
- A grievance log. Record every beneficiary complaint, what you did, and when. Patterns you can see are patterns you can fix before a State Health Agency sees them.
- Claim-to-payment tracking. Claim payment by a State Health Agency typically runs 15 to 30 days from submission. Anything persistently outside that window is a signal — either your submissions have a defect, or there is an issue at the SHA that you need to raise. Hospitals that do not track this discover a problem months of cash flow later.
The NABH connection
NABH accreditation is increasingly treated as a quality requirement for empanelment under government healthcare schemes and insurance providers. The direction of travel is clear: quality accreditation and scheme participation are converging.
The practical implication for hospital planning is that NABH accreditation should not be viewed as a separate, optional, later-stage project. It is becoming infrastructure for revenue access. A hospital that builds NABH-grade documentation discipline from commissioning tends to pass PMJAY audits comfortably, because the underlying systems — medical records, infection control, clinical protocols, indicator data — are the same systems.
The same is true at the foundation: valid clinical establishment registration and current statutory licences are eligibility preconditions, and a lapsed fire NOC or biomedical waste authorisation can surface during a scheme inspection rather than at renewal.
class="attachment-full size-full wp-image-6887" alt="" srcset="https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm.webp 1000w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-300x180.webp 300w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-768x461.webp 768w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-125x75.webp 125w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-480x288.webp 480w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-24x14.webp 24w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-36x22.webp 36w, https://www.hospertz.com/wp-content/uploads/2026/10/abha-id-capture-hospital-admission-abdm-48x29.webp 48w" sizes="(max-width:767px) 480px, (max-width:1000px) 100vw, 1000px" /> ABHA ID being captured at hospital admission as required for ABDM-compliant PMJAY claims

Our doctors, healthcare architects and NABH consultants will review your plan, budget and timeline.
If you receive a show-cause or suspension notice
Do not wait, and do not treat it as routine correspondence.
Respond within the stated timeline with documentation, not explanation. Pull the complete clinical file for every claim named. Where you find a genuine error, say so plainly, state what you have fixed, and show the control you have introduced to prevent recurrence — regulators respond far better to demonstrated correction than to denial. Where you believe the flag is a system error, evidence it specifically.
And keep the response factual. Inspection and disciplinary records become part of your file and are referenced in future proceedings.
Hospertz tipMake the pre-submission claim check a named role on the duty roster, not a shared responsibility. In the hospitals we see passing audits comfortably, one person signs off every PMJAY claim before submission and that sign-off is recorded. Shared ownership of this control is the same as no control.
The strategic view
PMJAY is not going to get looser. Scheme coverage keeps expanding — it now includes all senior citizens aged 70 and above regardless of economic status through the Ayushman Vay Vandana card — and enforcement has scaled alongside it. The ₹676.14 crore in blocked claims is the system working as designed.
For a well-run hospital, that is good news. Tighter enforcement removes competitors who were winning on lax billing rather than on care, and the compliance burden is genuinely manageable with the seven systems above.
The hospitals that get hurt are the ones treating PMJAY as a volume tap rather than a contract with documentation obligations.
If you are planning a new hospital and expect PMJAY to be a meaningful part of your case mix, build these systems into your SOPs at commissioning. Retrofitting compliance culture into a running hospital is far harder than starting with it. Our full guide to hospital empanelment covers the application process across PMJAY, TPAs and corporate panels.
Written by Dr. Vishal Jadhav, Founder & Director, Hospertz India Pvt Ltd. Last reviewed: October 2026.
Planning a hospital with PMJAY volume in your business case? Hospertz helps doctors and healthcare investors build empanelment-ready hospitals across India — from feasibility and licensing through to quality systems and commissioning. Get a free consultation →
Related reading: National Health Authority
Frequently asked questions
What is the most common reason PMJAY claims are rejected?
Documentation that does not support the package claimed, followed closely by ABHA identity mismatches. Every HBP code implies a clinical pathway, so a surgical package needs the operative notes, anaesthesia record, implant details and discharge summary in the file. Thin files on high-value packages reliably attract an audit.
Can a hospital ask a PMJAY beneficiary for a deposit if it is refunded later?
No. The hospital cannot collect any additional payment from a beneficiary, and a refunded deposit is still a violation of the empanelment MoU. Because beneficiaries complain about this directly, it is one of the fastest routes to suspension. Display the no-payment rule in the admission area in the local language and audit your receipt book monthly against PMJAY admissions.
Is ABDM integration mandatory for PMJAY empanelment?
In practice, yes. ABDM integration is now effectively a precondition for empanelment and claims processing, and hospitals that are not compliant face claim rejections and de-empanelment risk. Patients must be registered using their ABHA ID at the time of admission.
How long should PMJAY claim payment take?
Claim payment by a State Health Agency typically runs 15 to 30 days from submission. Anything persistently outside that window is a signal — either your submissions have a defect or there is an issue at the SHA to raise. Hospitals that do not track claim-to-payment discover the problem months of cash flow later.
What should we do on receiving a show-cause or suspension notice?
Respond within the stated timeline with documentation rather than explanation. Pull the complete clinical file for every claim named. Where you find a genuine error, say so plainly, state what you have fixed and show the control introduced to prevent recurrence. Keep the response factual — disciplinary records become part of your file and are referenced in future proceedings.
class="attachment-full size-full wp-image-6876" alt="" srcset="https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7.png 500w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-300x300.png 300w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-150x150.png 150w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-75x75.png 75w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-480x480.png 480w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-24x24.png 24w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-36x36.png 36w, https://www.hospertz.com/wp-content/uploads/2026/10/vishal-Jadhav-7-48x48.png 48w" sizes="(max-width:767px) 480px, 500px" /> Founder and Director of Hospertz. After a career in medicine, Dr. Vishal moved into corporate healthcare and now leads a team of healthcare architects, NABH consultants and project managers who plan and build hospitals, clinics and diagnostic centres across India.
Related guides
Turn this guide into a plan for your hospital.
Get a free first consultation on feasibility, licences, budget and timelines from the Hospertz team in Mumbai, Bhopal or Chhattisgarh.



